
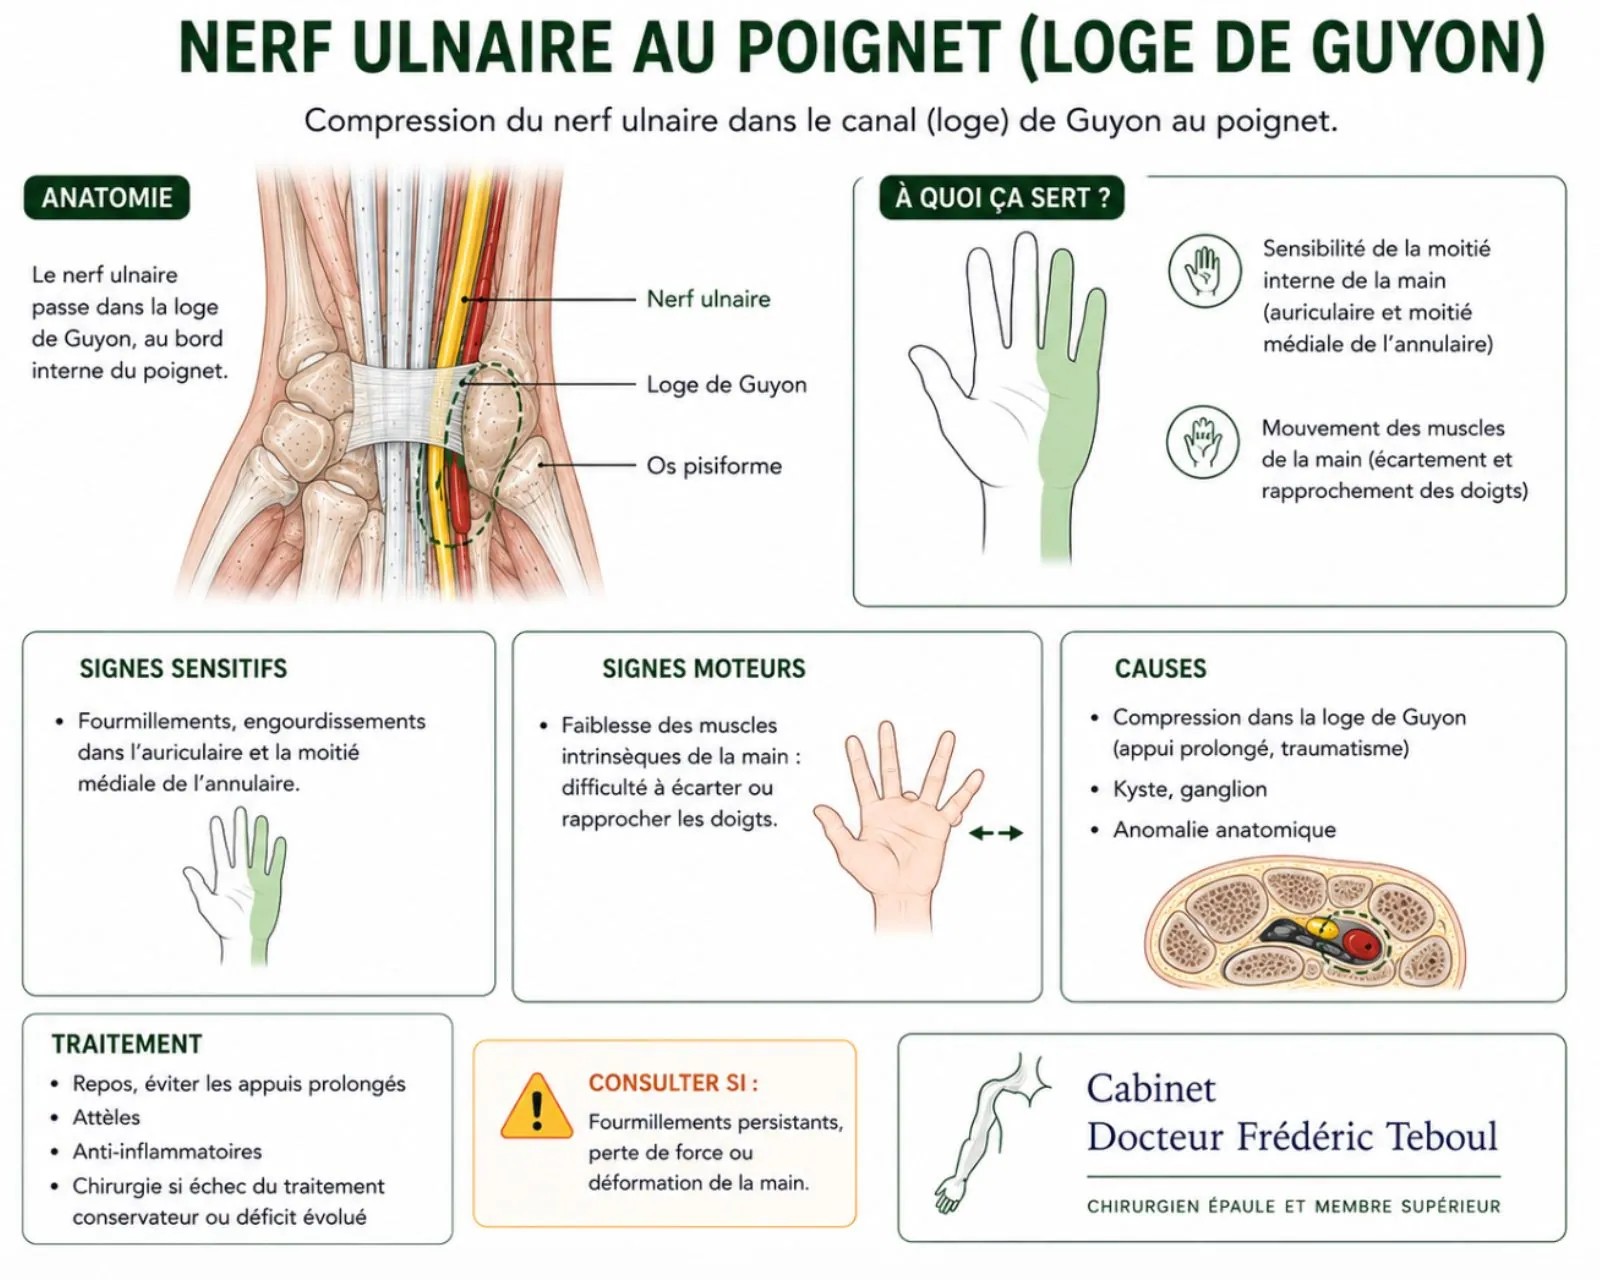
Intermittent tingling in the little finger and along the edge of the hand, a hand that loses strength, sometimes after long bike rides or repeated pressure on the heel of the palm. You may hear about the "canal of Guyon," a name little known to the public and not really accurate: it is a passageway without compression, not a canal. The motor branch, on the other hand, can be selectively compressed at an arch, beyond Guyon's canal.
This is a compression of the ulnar nerve — the same one responsible for cubital tunnel syndrome at the elbow — but this time located at the wrist. This article explains what characterizes it, how it is distinguished from its two far more common cousins, and why, here, looking for a local cause is especially important.
The ulnar nerve, from elbow to wrist
The ulnar nerve is one of the three main nerves of the hand. From the elbow, it runs down the forearm to the wrist, which it crosses through a small passage on the outer edge, on the little-finger side: Guyon's canal. The motor branch of the ulnar nerve can be compressed beyond Guyon's canal — the label "canal" is a semantic error that has persisted for decades.
This nerve is already familiar on this site for another reason: its far more common compression at the elbow, cubital tunnel syndrome. Guyon's canal is, in a sense, the lower version of it — much less common, but with its own rules.
A distinctive feature that explains the variety of presentations. Just before or within the canal, the ulnar nerve divides into two branches: a mainly sensory branch (for sensation in the little finger and the edge of the hand) and a mainly motor branch (for many small muscles of the hand). When the nerve is compressed, what is seen most is weakness and paralysis of the small muscles of the hand, because the compression sits beyond the canal, at an arch.
The symptoms
A loss of strength in the hand, difficulty spreading and bringing the fingers together, a weaker thumb-to-index pinch.
In advanced cases, muscle wasting along the edge of the hand and the beginning of clawing of the last two fingers.
The sign that makes the difference from the elbow
This is the article's first key point, and a genuine diagnostic landmark. Since the ulnar nerve can be compressed at the elbow as well as at the wrist, how do you know where? One simple sign points strongly in one direction.
The back of the hand: spared at the wrist, affected at the elbow
In Guyon's canal syndrome, the back of the hand, on the little-finger side, keeps normal sensation. The tingling is limited to the palm side.
The reason is anatomical and elegant: the small branch that provides sensation to the back of the hand leaves the nerve several centimeters before Guyon's canal. It therefore escapes any compression located within the canal. A compression at the elbow, higher up, also affects this branch — and so the back of the hand.
In practice: tingling limited to the palm → more likely the wrist; tingling that includes the back of the hand → more likely the elbow. A simple landmark, which the examination confirms.
The causes: here, you often have to look
This is the second key point, and what most distinguishes Guyon's canal from other nerve compressions. In carpal tunnel or cubital tunnel syndrome, the compression is usually "idiopathic" — with no identifiable local cause. Beyond Guyon's canal, by contrast, a specific cause is frequently found, and it must be actively sought.
Prolonged, repeated pressure on the heel of the palm
The classic case is the long-distance cyclist, whose hand presses on the handlebars — hence the vivid name "handlebar palsy." Using crutches, vibrating tools, or leaning at work has the same effect.
A synovial cyst in the canal
This is one of the most common local causes, and it is treated by removing the cyst.
A fracture or the aftermath of a fracture
In particular the hook of a bone called the hamate, which borders the canal.
How often these local causes occur changes the approach: at Guyon's canal, imaging is not a luxury; it is often necessary so as not to miss a cyst or a fracture that will need treatment. See the article on lumps and cysts of the fingers.
The diagnosis
It locates the tingling (palm only, or the back as well), tests the strength of the small muscles of the hand, and looks for a mass or a pressure point on the edge of the palm. This is what points the way first.
It confirms the nerve involvement, locates it at the wrist, and gauges its severity.
Ultrasound and MRI are particularly useful here to look for a cyst, a bone abnormality, or another local cause. This is what sets this work-up apart from that of other compressions.
The treatment
Without surgery, when the cause is pressure
When the compression is linked to a mechanical overload — cycling, repeated pressure — the first-line treatment is to remove that pressure, and it is often effective:
Avoid pressure on the heel of the palm; adapt the movement or the workstation.
Change your sporting practice: for the cyclist, change hand position, review the handlebar setup, wear padded gloves, vary your grip.
A wrist splint can help reduce the pressure, and relative rest lets the nerve recover.
In these mechanical cases caught early, the tingling often eases quickly once the cause is removed.
Surgery, when there is a local cause or a failure of other treatment
Surgery is indicated when there is a structural cause to remove — a cyst, the aftermath of a fracture — or when conservative treatment fails and a deficit persists. It involves releasing the ulnar nerve from proximal to distal, including the motor branch pinched between a small cyst and the fibrous arch of the intrinsic muscles, and removing the cause of the compression when there is one.
Why not to wait too long when the hand weakens
A principle shared by all nerve compressions applies here too: tingling recovers well, but strength returns more slowly and less completely if the weakness is long-standing.
When muscle wasting or a loss of strength sets in, you should not wait too long: the longer the motor involvement has been present, the greater the risk of lasting effects. Tingling alone allows for more patience.
The full picture
This table sums up the article: at the wrist, looking for the local cause and monitoring the strength of the hand are the two priorities.
Recovery
This question is too specific and must be handled case by case: visit our knowledge center to explore cases set in context.
Frequently asked questions
Glossary
A small passage at the wrist, on the little-finger side, where the ulnar nerve runs and where it can be compressed.
One of the three main nerves of the hand; controls sensation in the little finger and many small muscles.
Compression of the same ulnar nerve, but at the elbow — the most common form.
Compression at Guyon's canal from prolonged pressure of the palm, typical of cyclists.
A small wrist bone bordering Guyon's canal; a fracture of it can compress the nerve.
A small pocket of fluid that can form near a joint and compress the nerve within the canal.
References
Guyon Canal Syndrome. StatPearls. 2023 — rare compression of the distal ulnar nerve; motor, sensory or mixed presentation depending on the zone; the distinction from cubital tunnel syndrome rests on the sparing of the back of the hand
Guyon's Canal Syndrome (2025 reviews) — the dorsal cutaneous branch of the ulnar nerve arises 5 to 8 cm before the canal, which explains why the back of the hand stays normal in compression within the canal
Guyon Canal Syndrome. Physiopedia — handlebar palsy in cyclists from handlebar pressure; classification into three zones (motor, mixed, sensory) depending on the site of compression
Anatomy, Hand, Guyon Canal. StatPearls — synovial cysts account for roughly 30 to 45% of the causes of Guyon's canal syndrome
Ulnar Nerve Compression in Guyon's Canal by Ganglion Cyst. 2021 — a cyst can acutely compress the nerve; early decompression with removal is recommended for full recovery
Guyon canal etiologies — fracture of the hook of the hamate, sequelae of carpal fractures, lipoma, ulnar artery aneurysm among the structural causes to look for
Long-term results of Guyon's canal release according to the cause
Prevention of handlebar palsy in cyclists (equipment, ergonomics)
Reviewed and approved by Dr Frédéric Teboul, surgeon of the hand, brachial plexus and peripheral nerves, member of the Académie Nationale de Chirurgie.
Last updated: August 20, 2026
Disclaimer. This article is for information purposes. It does not replace a medical consultation. A loss of strength or muscle wasting of the hand warrants specialist advice without delay.
Author of this publication
Every piece of content is signed by its author and reviewed before publication.
 Author
Dr Frédéric Teboul
Hand surgeon — specialist in the brachial plexus and peripheral nerves