

You wake up at night with a numb hand. You shake it to "wake it up." You drop objects without understanding why. And you wonder whether surgery is really unavoidable.
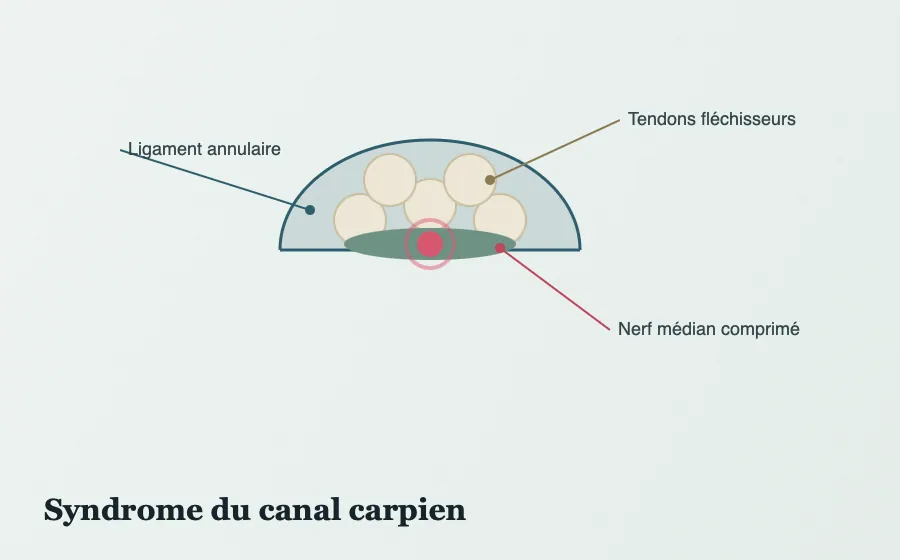
The carpal tunnel, in one image
The carpal tunnel is an inextensible tunnel at the wrist. Its floor and walls are formed by the carpal bones; its roof by a thick ligament, the flexor retinaculum. Inside run the tendons that bend the fingers, and one nerve: the median nerve.
The key word is "inextensible." The tunnel cannot enlarge. If its contents swell — thickening of the tissue around the tendons, edema — the pressure rises, and the nerve is the first to suffer.
It is not only mechanical compression. Added to it are a reduced blood supply to the nerve, and then damage to the nerve fibers themselves. This is why the symptoms are not merely a nuisance, but genuine nerve injury, which can become irreversible.
The warning signs
The central symptom is tingling and numbness in the territory of the median nerve: the palmar surface of the thumb, index and middle finger, and half of the ring finger. The little finger is spared — a key clue for orientation.
Three features are highly suggestive:
The symptoms wake you at night. This is the most characteristic sign.
The need to shake the hand to relieve it, a gesture that patients describe spontaneously.
The pain can radiate up the forearm, sometimes as far as the elbow or shoulder — which often misleads the diagnosis.
At a more advanced stage, a loss of pinch strength appears, along with clumsiness and objects slipping from the hand.
What should not wait
—Wasting of the muscle at the base of the thumb — a hollow forming where there was once a bulge. This is the sign of advanced nerve injury.
—A permanent loss of sensation, present during the day as well and no longer only at night.
—An established loss of strength with repeated dropping of objects.
These signs are not a life-threatening emergency, but a matter of timing. Beyond a certain stage, part of the deficit may not recover, even after a technically successful operation.
How the diagnosis is made — and the debate around nerve conduction studies (EMG)
The diagnosis rests first on the history and clinical examination: the territory of the symptoms, provocation tests (Phalen's maneuver, Tinel's sign), and looking for weakness and muscle wasting at the base of the thumb.
One point is worth knowing, because it is evolving. The American guidelines published in May 2024 state, with a high level of evidence, that a validated clinical score — the CTS-6 — can be enough to make the diagnosis, without systematic recourse to ultrasound or electromyography. AAOS 2024 These same guidelines advise against MRI as a first-line investigation (moderate evidence).
This does not mean that electromyography is useless. In France, it retains a role that goes beyond diagnosis alone: assessing severity, documenting the condition before a procedure, and serving as an important element in occupational-disease recognition files.
Is the computer keyboard to blame?
This is the most frequent question in consultation, and the answer will surprise many readers.
The working group that drafted the 2024 American guidelines concludes that, in the absence of reliable data, no solid evidence establishes an association between heavy keyboard use and carpal tunnel syndrome. AAOS 2024
A point of honesty: this is a working-group opinion, issued for want of sufficient evidence — not a demonstration that the keyboard is entirely blameless. The correct wording is: nothing today allows this link to be affirmed.
Other factors, on the other hand, are well identified: highly repetitive movements with a strong grip or exposure to vibration, obesity, diabetes, hypothyroidism, rheumatoid arthritis, kidney failure, pregnancy and menopause, as well as an anatomical or familial predisposition.
Non-surgical treatments: what they actually do
The night splint
A splint holding the wrist in a neutral position, worn mainly at night, is a simple, well-tolerated first-line treatment in mild to moderate forms. The available data show a real benefit on symptoms.
But the head-to-head comparison is unambiguous: the 2024 Cochrane review, which pooled 14 randomized trials and 1,231 participants, concludes that surgery relieves symptoms significantly better than a splint. Cochrane 2024
The corticosteroid injection
This is where the information available online is most misleading. You often read that an injection can provide relief "for more than a year."
The 2024 guidelines state the opposite, with a high level of evidence: corticosteroid injection provides no long-term improvement in carpal tunnel syndrome. AAOS 2024
That does not mean it is useless. It genuinely relieves symptoms in the short term, and can make full sense in a pregnant patient, in a patient who does not wish to have surgery, or while awaiting a procedure. But it does not solve the problem over the long run.
What has not proven itself
The 2024 guidelines are explicit about several frequently proposed treatments:
PRP (platelet-rich plasma) injections provide no lasting benefit — high level of evidence.
Therapeutic ultrasound provides no long-term improvement.
Acupressure, thermotherapy, magnet therapy and nutritional supplements do no better than a placebo.
Oral corticosteroids can improve symptoms transiently, but remain less effective than a local injection and carry the risk of systemic effects.
Physical therapy — nerve gliding exercises, mobilizations — rests on low-quality evidence. It carries little risk and can accompany other treatments, but does not constitute a treatment in its own right.
The operation: what has changed
The principle has stayed the same for decades: completely divide the ligament that forms the roof of the tunnel, in order to decompress the median nerve. What has changed is the way it is done.
You can be operated on while awake, under local anesthesia alone
This is probably the most useful piece of information in this article, and it is rarely written down.
The 2024 American guidelines state, with a high level of evidence, that carpal tunnel release can be performed under local anesthesia alone. AAOS 2024
No general anesthesia, no anesthesia of the whole arm: a local anesthetic, comparable to that used for dental care. This approach is at the heart of what is known as minimally invasive surgery and office-based surgery, a field that Dr Frédéric Teboul has helped develop in France.
Open, mini-open or endoscopic?
The 2024 guidelines are clear on one point: there is no difference in outcome, as reported by patients, between a mini-incision release and an endoscopic release — high level of evidence. AAOS 2024
The difference lies elsewhere: in the time to resume activities, in scar-related discomfort during the first few weeks, and in the surgeon's experience with each technique. The frequently cited figure of a return to work about one week earlier after endoscopy needs to be precisely sourced.
The guidelines also specify that the division must be complete whatever the technique, and advise against routine associated procedures such as epineurotomy or tenosynovectomy, given the lack of demonstrated benefit.
Should you have surgery? What the largest trial ever conducted says
In June 2025, a Dutch randomized trial provided the most robust answer we have. Conducted in 31 hospitals, it followed 934 patients randomly assigned to two strategies: starting with surgery, or starting with an injection — with, in both cases, the possibility of additional treatments afterward. DISTRICTS 2025
Two lessons, which must be read together.
The first: starting with surgery gives a better chance of cure at 18 months.
The second, just as important: even in the operated group, nearly four patients out of ten did not meet the criterion for cure at 18 months. And at least one adverse event occurred in 86% of patients in the surgery group, versus 85% in the injection group — near-identical figures, and high in both cases.
What "cured" means here: a score below 8 on a validated six-item clinical scale. That is not the same as "as before," nor is it "no improvement" for the others.
Also of note: the 2024 Cochrane review concludes that surgery does better than a splint, but that it remains uncertain whether it does better than an injection. Its data stop in November 2022 — that is, before the Dutch trial, which provides precisely this answer. Cochrane 2024
The risks, without downplaying them
The complications described after carpal tunnel release are scar pain, pain along the edges of the tunnel (often called pillar pain), superficial infections, surgical nerve injuries and complex regional pain syndrome. Serious complications remain uncommon.
The rates of lasting "good to excellent" results usually reported lie between 70 and 90%. True recurrences are rare; when discomfort persists, it calls for restarting the diagnostic reasoning from the beginning rather than concluding a technical failure.
One clarification from the 2024 guidelines: antibiotic prophylaxis is not routinely indicated to prevent surgical-site infection (limited evidence). AAOS 2024
After the operation
Three of the 2024 recommendations run counter to still-widespread practices:
Do not routinely immobilize the wrist with a splint or sling after the procedure — moderate evidence. Immobilization increases the risk of stiffness without improving the result.
Do not routinely prescribe supervised rehabilitation after a release — moderate evidence.
Use nonsteroidal anti-inflammatory drugs and/or acetaminophen for postoperative pain — high evidence.
What recovers, and what does not
This is the most important section for making a decision, and the one almost no site addresses honestly.
In broad terms: the night-time awakenings and the tingling often subside quickly. Fine sensation and strength take much longer. And when muscle wasting at the base of the thumb is already established, part of the motor deficit may persist despite a properly performed decompression.
This is what makes the question not only "should surgery be done," but "at what point does waiting start to cost something."
Frequently asked questions
Glossary
The nerve that passes through the carpal tunnel and provides sensation to the thumb, index and middle finger and part of the ring finger.
The thick ligament forming the roof of the carpal tunnel. It is this that is divided to decompress the nerve.
The muscular bulge at the base of the thumb. Its wasting is a sign of advanced nerve injury.
A validated clinical score used to assess the likelihood of carpal tunnel syndrome based on the examination.
A test measuring nerve conduction, used to assess the severity of the injury.
References
American Academy of Orthopaedic Surgeons. Management of Carpal Tunnel Syndrome — Evidence-Based Clinical Practice Guideline. Published May 18, 2024 (replaces the 2016 edition). Literature search closed on November 17, 2022.
Palmbergen WAC, Beekman R, Heeren AM, et al.; Dutch CTS study group. Surgery versus corticosteroid injection for carpal tunnel syndrome (DISTRICTS): an open-label, multicentre, randomised controlled trial. Lancet. 2025;405(10495):2153-2163. PMID 40517008
Lusa V, Karjalainen TV, Pääkkönen M, Rajamäki TJ, Jaatinen K. Surgical versus non-surgical treatment for carpal tunnel syndrome. Cochrane Database Syst Rev. 2024;1(1):CD001552. PMID 38189479
Padua L, Coraci D, Erra C, et al. Carpal tunnel syndrome: clinical features, diagnosis, and management. Lancet Neurol. 2016;15(12):1273-1284
Goubier JN, Teboul F, Dubert T. Patient information in carpal tunnel release. Chirurgie de la Main. 2007;25(6):286-292
Atroshi I, et al. Prevalence of carpal tunnel syndrome in a general population. JAMA. 1999 — to be confirmed as the source of the prevalence figure
JAMA trial, 176 patients, splint vs surgery
Neurology trial, 50 patients, surgery vs injection
Nature Reviews Disease Primers 2024, pathophysiology
Article authored and reviewed by Dr Frédéric Teboul, hand, brachial plexus and peripheral nerve surgeon, member of the Académie Nationale de Chirurgie.
Last updated: August 20, 2026
Disclaimer. This article is intended for information purposes. It does not replace a medical consultation. Only a clinical examination can establish a diagnosis and choose a treatment suited to your situation.
Author of this publication
Every piece of content is signed by its author and reviewed before publication.
 Author
Dr Frédéric Teboul
Hand surgeon — specialist in the brachial plexus and peripheral nerves